Creatine is a naturally occurring compound found in muscle tissue that plays a vital role in cellular energy metabolism. While traditionally recognized for its benefits in enhancing skeletal muscle function and exercise performance, recent research has highlighted its potential therapeutic applications in various medical fields. This study reviews the available literature to assess the current state of knowledge regarding creatine’s medical uses and outlines directions for future research. Evidence has demonstrated a correlation between low creatine levels and reduced mental well-being, suggesting a role in the central nervous system. Notably, creatine has been explored as a potential antidepressant—both as a standalone treatment and as an adjunct to selective serotonin reuptake inhibitors (SSRIs)—owing to its newly discovered function as a neurotransmitter. Additionally, long-term investigations into creatine’s molecular mechanisms in the brain have prompted its study in stroke management, where it may support both prevention in high-risk populations and post-stroke rehabilitation. In the context of chronic heart failure, creatine has been linked to cardiomyocyte metabolic dysfunction, particularly regarding disruption of the creatine/phosphocreatine/ATP shuttle. Although studies examining creatine supplementation in cardiovascular disease have produced mixed results, the compound shows promise as a supportive therapy. However, further research is necessary to confirm its efficacy and safety across these medical applications.
Creatine is a naturally occurring compound primarily stored in skeletal muscles, which contain approximately 95% of the body’s total creatine content. Smaller amounts are found in the liver, kidneys, brain, and testes. It is also obtained exogenously from dietary sources—particularly red meat and seafood—at an average rate of about 1 gram per day [1]. As creatine is almost exclusively found in animal products, individuals following vegetarian or vegan diets typically have lower serum and muscle creatine levels than omnivores [2].
Over the past several decades, creatine has become one of the most extensively studied and widely used nutritional supplements. Its prevalence of use ranges from 15% to 40% among athletes and military personnel due to its well-documented benefits in enhancing athletic performance and promoting muscle hypertrophy [1, 3].
Creatine is a nitrogen-containing compound synthesized endogenously from the amino acids glycine, arginine, and S-adenosylmethionine, which serves as a methyl group donor. It is classified as a non-protein amino acid and is primarily synthesized in the liver and kidneys, although smaller amounts are also produced in the pancreas, testes, and brain [4]. In the body, creatine exists in two main forms: approximately 40% as free creatine and 60% as phosphocreatine. The latter serves as a rapid source of high-energy phosphate groups to regenerate adenosine triphosphate (ATP) from adenosine diphosphate (ADP), particularly during short-duration, high-intensity activities [1]. This reaction is critical for sustaining energy production during vigorous physical exertion [1, 3]. The biosynthetic pathway of creatine is outlined in Figure 1.
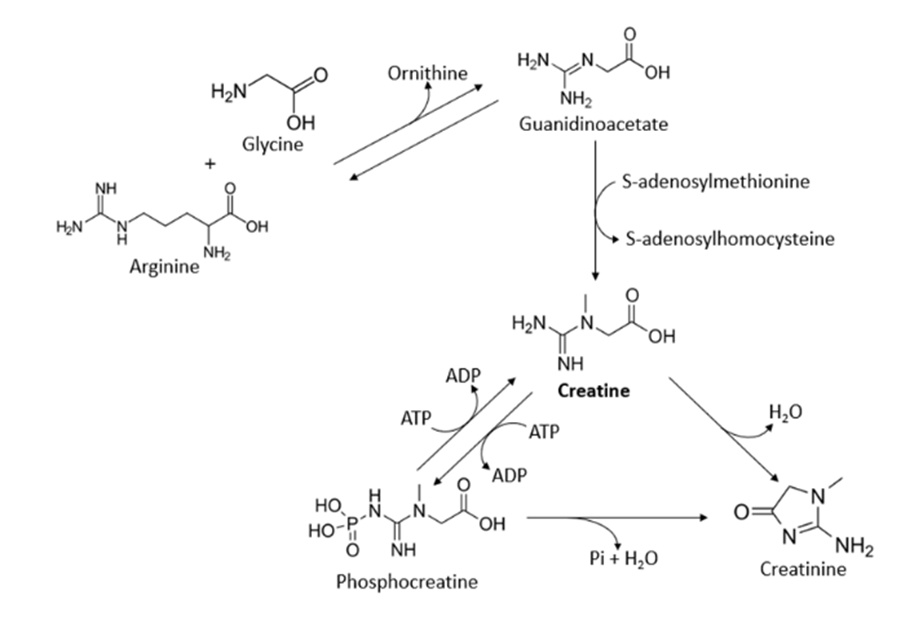
Figure 1. Pathway of creatine synthesis based on Kreider et al. [3]
Extensive research has affirmed the efficacy of creatine supplementation in improving athletic performance. Numerous studies have reported significant increases in muscular strength and power, particularly in anaerobic activities such as sprinting and resistance training. Additionally, creatine promotes muscle hypertrophy by stimulating protein synthesis, making it a valuable supplement for bodybuilders [5]. Emerging evidence also suggests that creatine may enhance muscle recovery by reducing post-exercise muscle damage and inflammation [3, 6]. Furthermore, the improved ATP resynthesis associated with creatine can buffer intramuscular acidosis, potentially mitigating fatigue and preserving performance during strenuous activity [5].
Beyond its established role in sports and exercise, creatine has attracted increasing attention for its potential therapeutic applications in medicine. In recent years, research has expanded into exploring its efficacy in neurology, cardiology, psychiatry, and geriatrics [1]. This review aims to evaluate creatine’s emerging clinical applications, examine its underlying mechanisms, and assess the current evidence base to determine whether its benefits in these settings outweigh potential risks.
Numerous dosing protocols have been examined to understand their effects on creatine levels and associated performance improvements. Typically, supplementation involves two phases: loading and maintenance. The loading phase involves a high dose of creatine for a brief period—generally 5-7 days—to rapidly increase muscle creatine stores. The usual daily dose during this phase ranges from 20 to 25 grams, taken in smaller portions throughout the day. Following the loading phase, the daily dose is reduced to a maintenance level of 3-5 grams to sustain the elevated creatine stores [3, 5]. Once supplementation is discontinued, creatine levels typically return to baseline within 4-6 weeks [3]. However, there is ongoing debate regarding the necessity of the loading phase. While it is effective in rapidly boosting muscle creatine levels by 20%-40% [5], a study by Hultman et al. [7] suggested that smaller, sustained doses can achieve similar results over time, though the increase is more gradual. Therefore, the dosing approach may be adjusted based on personal goals.
Creatine, whether consumed through food or supplements, is absorbed in the gastrointestinal tract. Due to its similarity to amino acids, it is believed that creatine crosses the intestinal barrier via amino acid or peptide transporters [8]. However, specific creatine transporters in the intestine have also been identified [9]. Once absorbed, creatine enters the bloodstream and circulates, where various tissues take it up. Plasma creatine levels rise within an hour of ingestion, reach a peak, then gradually decrease [3]. This process involves two creatine transporters, CreaT1 and CreaT2, which are predominantly expressed in the target tissues. CreaT1 is found in skeletal muscle, brain, heart, kidneys, and testes, while CreaT2 expression is mainly confined to the testes [10]. Creatine monohydrate, the most commonly researched form, is nearly 100% bioavailable, meaning it is almost fully absorbed and either utilized by the body or excreted in urine. The amount of creatine retained by the body can be calculated by subtracting the amount excreted through urine from the total intake [11]. Several factors, including the supplement’s form, other nutritional components, and individual characteristics, can influence creatine’s bioavailability.
Creatine is generally regarded as safe when taken according to recommended guidelines, though concerns about potential side effects persist. The most frequently reported adverse effect is weight gain, which initially results from water retention and later from increased muscle mass, a desired effect for athletes [3, 5]. Gastrointestinal issues such as bloating, diarrhea, and nausea have been reported, but there is no solid evidence on their frequency [3]. Some researchers have suggested that creatine may cause muscle cramps or dehydration due to fluid shifts and electrolyte imbalances, but clinical studies have not confirmed these claims [3, 12]. Concerns have also been raised about the potential for kidney damage from creatine supplementation, but extensive research has largely dismissed these worries [13].
The incidence of mental health disorders in Europe continues to rise, accounting for 13.9% of the total disease burden in 2015 [14]. The COVID-19 pandemic has exacerbated this issue, with many individuals experiencing worsening psychiatric symptoms [15]. While traditional treatments for mental health disorders, such as neurotransmitter reuptake inhibitors, remain widely used [16], there is growing interest in finding new compounds that may be effective in preventing and treating these conditions. This interest is driven by the rising challenge of drug-resistant depression and the profound impact that depression has on overall health, which in turn places greater strain on healthcare systems [17].
To explore the potential benefits of creatine in treating depressive behaviors, it’s essential to understand the underlying molecular mechanisms. The brain, which is highly energy-demanding and consumes around 20% of the body’s total energy, houses a specific isoform of creatine kinase (BB-CK) that plays a critical role in the Cr/PCr/ATP energy shuttle. This suggests that creatine may be key in maintaining normal energy levels in the brain [18, 19].
Animal studies have been pivotal in elucidating the mechanisms underlying brain creatine metabolism. One study used proton magnetic resonance spectroscopy (1H MRS) in rats with induced depression to assess creatine and phosphocreatine levels. The results indicated that these levels were notably lower in brain regions such as the medial prefrontal cortex (mPFC), hippocampus, and amygdala [20]. The rats were subjected to a single-prolonged stress (SPS) model, which involves a series of stressful events (such as immobilization and forced swimming) to induce a state resembling post-traumatic stress disorder (PTSD) and depressive behaviors, making them ideal models for studying depression [21].
In another experiment, administering creatine to depressed rats resulted in a reduction of depressive symptoms, though this effect was observed only in female rats [22]. Prior research has also demonstrated that creatine functions as a neurotransmitter in rat brains, accumulating and being released in response to action potentials. This process is facilitated by sodium cations, aligning with the role of the Na+-dependent creatine transporter (SLC6A8). Interestingly, when sodium channels were blocked with tetrodotoxin (TTX), creatine secretion was halted. On the other hand, blocking potassium channels with 4-aminopyridine (4-AP) enhanced creatine transmission [23].
Further studies revealed that creatine’s antidepressant effects were blocked by inhibitors of key protein kinases involved in depression, such as PKA, PKC, CAMK-II, and MEK1/2 [24]. Additional research by the same team identified the intracellular signaling pathways, including Akt, mTOR, and GSK3, as crucial for mediating creatine’s beneficial effects on mental health. When PI3K or mTOR inhibitors were administered, these effects were no longer observed in rats, confirming the importance of these pathways [25].
In humans, similar results have been observed, with lower creatine concentrations in the mPFC correlating with a higher likelihood of depression. When creatine levels in the brain are reduced, depressive symptoms are often more severe [26]. Population-based studies have also demonstrated a link between creatine intake and reduced depression risk. Specifically, individuals who consumed more than 0.7 grams of creatine daily had a 30% lower chance of developing depression compared to those consuming less than 0.26 grams [27]. Despite creatine’s limited ability to cross the blood-brain barrier, studies show that oral supplementation increases its concentration in both gray and white matter. This effect is observed after a single high dose or over four weeks of supplementation, with concentrations returning to baseline within three months after discontinuation [28].
Other studies have explored substances within the same metabolic pathway as creatine. One such study, using phosphorus-31 magnetic resonance spectroscopy and brain transverse relaxometry, showed that daily supplementation with 1,600 mg of S-adenosyl-L-methionine (SAMe), a creatine precursor, increased phosphocreatine concentrations and decreased transverse relaxation time. This suggests enhanced function of brain structures and increased energy activity, as prolonged relaxation time can indicate tissue atrophy. While SAMe had been recognized as an antidepressant since the 1990s, this particular study delved into the molecular mechanisms behind its therapeutic effects. Interestingly, significant gender differences were noted, with women experiencing a more pronounced treatment effect compared to men [29]. Additionally, a comparison between creatine and guanidinoacetic acid (GAA) supplementation found that GAA increased brain creatine levels more effectively than creatine alone. This might be attributed to GAA’s more efficient transport into the central nervous system, facilitated by various transporters, including SLC6A8, SLC6A6, GAT2, and passive diffusion, which enhances its bioavailability compared to creatine [30, 31].
Building on in vitro and healthy population studies, a pilot trial involving individuals with mental health disorders was conducted. After four weeks of creatine monohydrate supplementation (3-5 g/day), individuals with unipolar depression showed significant improvements in scores on the Hamilton Depression Rating Scale and the Clinical Global Impression Scale [32]. In patients with bipolar depression, six weeks of 6 grams/day creatine supplementation led to improvements in verbal fluency, although no changes were observed in other neuropsychological tests [33]. Notably, the studies involving creatine as an adjunct to traditional antidepressants like fluoxetine highlighted its supportive role. It’s important to mention that much of this research focused on female participants. However, some studies dispute creatine’s effectiveness when used alongside SSRIs for treating depression [19].
Creatine deficiency in the central nervous system is also being explored in relation to other psychiatric conditions. Lower creatine levels have been observed in the hippocampus and occipital white matter in individuals with PTSD and generalized anxiety disorder (GAD) [34]. While large, randomized trials are lacking in these populations, preliminary case reports and studies indicate that creatine supplementation may reduce symptoms of anxiety in patients previously resistant to treatment [18, 19].
A wide array of in vitro and animal model studies has provided valuable insights into the molecular mechanisms through which creatine operates in the central nervous system, its ability to cross the blood-brain barrier, and its metabolism. These studies, many utilizing magnetic resonance imaging, have identified specific brain regions related to mental health disorders where creatine deficiencies contribute to reduced brain bioenergetics [1].
Given the evidence, it is clear that creatine levels in the brain may influence mental health, and supplementation with creatine or its derivatives could offer therapeutic benefits for depression and other mental health conditions. Pilot studies with patients have consistently shown improvements in affective disorders with creatine supplementation [19]. However, a lack of clear guidelines, recommended dosages, or indications for creatine or its derivatives limits their widespread use. This is primarily due to insufficient data from large-scale trials, though many studies are currently underway. In the near future, we can expect new research, potentially including a meta-analysis, to provide conclusive evidence regarding creatine’s effects, paving the way for its broader use in clinical settings.
Stroke, which can be either hemorrhagic or ischemic (cerebral infarction), was the third leading cause of death and disability worldwide in 2019, accounting for 12.2 million new cases and 101 million prevalent strokes globally. Projections suggest that by 2050, the incidence and mortality from stroke could nearly double [35]. Consequently, there is a pressing need to develop new prevention and treatment strategies. Creatine supplementation may be a promising area of exploration, as it could help maintain energy availability within cells through the Cr/PCr/ATP system, which is vital for cellular energy homeostasis [36].
There has been some skepticism regarding the ability of oral creatine supplementation to effectively increase brain creatine levels, as research suggests that the brain depends less on exogenous creatine than muscles do [18]. However, two studies conducted on mice, discussed in the following section, demonstrate promising results for oral supplementation in reducing infarct volume following a stroke [37, 38].
One study by Zhu et al. [38] aimed to explore the effects of creatine on reperfusion and neuroprotection in a mouse stroke model. The researchers measured infarct volume, ATP, and creatine concentrations in ischemic and non-ischemic brain tissues, and markers of apoptosis, such as cytochrome c release and caspase-3 activation in the infarct area. While the study did not provide detailed information about the supplementation dosage, the results were encouraging. A 56% reduction in infarct volume was observed compared to the control group. Additionally, ATP and creatine levels were significantly higher in the ischemic brain regions, with a notable 56.3% reduction in ATP drop after ischemia. Creatine supplementation also inhibited cytochrome c release and caspase-3 activation, as shown by Western Blot analysis [38]. A subsequent study in humans, involving 7 days of supplementation with 20 grams of creatine per day (a typical loading dose), also demonstrated a significant reduction in plasma caspase-3 concentration and a notable increase in the antiapoptotic protein Bcl-2 [39, 40]. However, the precise mechanism behind creatine’s influence on these markers, whether direct or indirect, remains unclear.
In another mouse model study by Prass et al. [37], the focus was not only on nervous tissue changes but also on the effects of creatine on cerebral vascular function. They observed that creatine supplementation improved vasodilation in middle cerebral arteries, especially in response to acidosis (a condition that can occur in ischemic areas). Creatine-treated mice also exhibited faster recovery from ischemia, as shown by magnetic resonance imaging assessing blood flow and diffusion. Interestingly, the study found no differences in Cr/PCr/ATP concentrations between the creatine-treated and control groups in nervous tissue. Furthermore, the study highlighted a dose-dependent effect of creatine supplementation on reducing infarct volume. Notably, oral creatine supplementation reduced infarct volume by 42% compared with the control group, whereas intravenous creatine did not. The study also showed that prolonged supplementation (3 months) produced more significant effects than shorter durations (12 months) [37]. The results support further investigation into creatine’s long-term preventive potential in stroke patients.
Another critical study by Turner et al. [41] explored the impact of creatine supplementation on the excitability of corticomotor neurons and cognitive performance during reduced oxygen conditions (hypoxia). The study used a randomized, double-blind, crossover design with 15 healthy, right-handed participants who received 20 grams of creatine per day for 7 days (a typical loading dose). After exposure to 90 minutes of hypoxia (10% oxygen), neuropsychological assessments and neuroimaging were performed. The results confirmed that creatine supplementation increased creatine and phosphocreatine levels in the sensorimotor cortex, as confirmed by magnetic resonance spectroscopy. The neuropsychological tests revealed that creatine improved performance on tasks requiring complex attention during hypoxia. Additionally, creatine supplementation increased corticomotor excitability in the motor cortex of the first dorsal interosseous muscle compared with the control group [41].
Research into novel creatine derivatives is an exciting field, particularly for situations where the creatine transporter is impaired, and traditional supplementation may be insufficient [42]. These new compounds aim to improve the ability to increase Cr/PCr/ATP concentrations in brain tissue [43], enhancing creatine’s role as an energy buffer. Additionally, these derivatives may improve blood-brain barrier (BBB) penetration, allowing for higher central nervous system concentrations with lower dosages—an essential factor for patients with concurrent conditions requiring supplementation.
A significant concern for stroke survivors is the range of consequences they may face, including muscle weakness, sarcopenia [44], and psychological symptoms such as anxiety, depression, or PTSD [45]. This population requires specialized care and rehabilitation to improve their daily functioning and overall quality of life [46].
Butchart et al. [47] examined the effects of adding creatine supplementation to progressive resistance training (PRT) in stroke survivors, focusing on several aspects impacted by stroke, including body composition, exercise capacity, and anxiety levels. The study found that PRT alone positively affected muscle strength and thickness, improved balance and cognition, and reduced depression. When creatine was added to the regimen, the benefits were further amplified, with participants demonstrating improved walking performance and greater distance covered during the 6-minute walk test. This suggests that creatine supplementation may offer not only preventive benefits for stroke but also therapeutic effects for stroke survivors dealing with its consequences.
Despite these promising results, the studies exploring creatine’s prophylactic effects on stroke, as mentioned earlier, do not provide definitive proof of its benefits in stroke patients [37, 38]. However, they lay a solid foundation for larger-scale studies investigating the long-term use of creatine in high-risk populations. Such studies could provide clearer insights into the true effects of creatine on stroke outcomes and help resolve uncertainties regarding the differences between short-term and long-term creatine supplementation in managing cerebral ischemia [37]. Additionally, research into novel creatine derivatives [43, 48] may yield new insights into the protective role of creatine against cerebral ischemia, potentially reshaping current views of its therapeutic potential.
Another critical research direction for creatine’s use in central nervous system disorders is to address its poor ability to cross the blood-brain barrier [49]. Advances in developing new compounds or methods to improve the brain penetration of creatine monohydrate could optimize dosing regimens and reduce the risk of side effects associated with supplementation [30].
Heart failure (HF) is a major global health concern, affecting over 60 million people worldwide [50]. According to the consensus definition by various heart failure societies, HF is characterized by structural or functional cardiac dysfunction, as evidenced by elevated natriuretic peptides, and is often accompanied by pulmonary or systemic congestion. While HF is a complex syndrome influenced by many factors, hypertension and ischemic heart disease are recognized as major contributors to its development [51].
The heart relies on continuous ATP production to function correctly. Daily, the heart consumes about 6000 grams of ATP, approximately 20 times its own weight. If ATP production were to cease, the heart would deplete its immediate ATP stores within 2 to 10 seconds, leading to functional impairment [51, 52]. Therefore, maintaining adequate ATP levels is crucial, and the heart employs three primary mechanisms for ATP production: substrate utilization, the mitochondrial respiratory chain, and the creatine kinase (CK) energy shuttle [52]. The creatine kinase system is vital for ensuring a continuous ATP supply in cardiomyocytes, which is essential for proper heart function [51].
In failing hearts, however, ATP production is insufficient to meet cardiomyocyte demands, primarily due to altered cardiac metabolism and unfavorable remodeling [53]. Despite this, cardiomyocytes have protective mechanisms to mitigate the consequences of this energy imbalance, with one key mechanism being the creatine phosphate energy shuttle. Numerous studies suggest that this metabolic process is impaired in heart failure and may contribute significantly to the progression of the disease [54, 55].
It has long been recognized that both ATP and phosphocreatine (PCr) levels are diminished in animal models of heart failure (HF) and in human patients with the condition [56]. More recent advancements, especially studies using magnetic resonance spectroscopy instead of biopsies, have reinforced and clarified these findings [57, 58]. In addition to measuring these levels, another critical indicator of myocardial metabolic health is the PCr/ATP ratio. As expected, numerous studies have validated that this ratio is lower in individuals with HF [59, 60]. This suggests that markers such as the PCr/ATP ratio, along with PCr and creatine (Cr) concentrations, may provide valuable insights into the progression of HF. Samuel et al. [61] found that reduced ATP levels in cardiomyocytes are associated with an increased risk of fatal arrhythmias, while Bottomley et al. [62] reported that the ability to produce ATP via creatine kinase (CK) could predict HF severity and mortality. However, the utility of these markers is limited by their lack of specificity, as similar reductions may also occur in conditions such as type 2 diabetes [63]. Another concern is the clinical relevance of these markers, as assessing phosphorus content in the heart requires specialized equipment, trained professionals, and considerable financial investment [62].
A notable study by Ten-Hove et al. [64] examined the role of creatine in rodent hearts under stress. Mice lacking guanidinoacetate-N-methyltransferase (GAMT), the enzyme responsible for creatine synthesis, were subjected to ischemic conditions and inotropic stimulation using dobutamine. At baseline, there were no significant differences between the GAMT-knockout mice and wild-type controls in terms of systolic or diastolic function. However, under stress (ischemia/reperfusion and inotropic stimulation), the GAMT-deficient mice, which lacked the ATP-creatine shuttle, showed impaired cardiac function and a poorer recovery of contractile strength after reperfusion [64]. Similarly, Lygate et al. [65] generated a mouse model with elevated myocardial creatine levels by modifying the creatine transporter (CrT). These mice demonstrated better outcomes during ischemia/reperfusion, although there were no notable differences in the development of chronic HF. This suggests that the Cr/PCr/ATP shuttle is particularly crucial during short bursts of increased energy demand, such as during ischemic events, which are common in HF [52]. Other studies that have impaired the creatine shuttle have yielded similar results, reinforcing this conclusion [66, 67].
Given that HF is closely associated with metabolic dysfunction in the heart—particularly with disruptions in the Cr/PCr/ATP shuttle and CK flux—the question arises whether creatine supplementation could address these issues and improve both heart function and physical performance in individuals with chronic HF. While this approach seems plausible based on HF pathophysiology, existing research does not yet provide conclusive evidence, and several obstacles remain.
One of the major challenges in utilizing creatine supplementation as an adjunct therapy in heart failure (HF) is the complexity of increasing intramyocardial creatine levels. Some studies suggest that this process is hindered by downregulation of the creatine transporter (CrT) at both the plasma and mitochondrial membranes. CrT levels are closely associated with intracellular creatine concentrations, which could limit the effectiveness of supplementation [65].
In line with this, Boehm et al. [68] found that increased creatine intake did not raise myocardial creatine levels in rats, suggesting that oral supplementation might not be as effective as expected. Lygate et al. [65], in their study investigating the impact of creatine on myocardial function in the context of HF and ischemia, also demonstrated that upregulating CrT expression (rather than oral supplementation) led to elevated myocardial creatine levels. These studies highlight the importance of CrT in regulating creatine levels in the heart and suggest that targeting CrT could be a promising therapeutic approach for HF. However, this issue also complicates the therapeutic use of creatine. Some experimental studies have shown that, even with increased myocardial creatine levels, no protective effect was observed in preventing hypertrophy, left ventricular dilation, or impaired function after induced myocardial infarction.
On the other hand, in ischemic reperfusion models, creatine supplementation appeared to provide significant protection, with treated mice showing near-identical resistance to damage as those that underwent ischemic preconditioning [65, 69, 70]. Similarly, a study combining ribose supplementation with elevated myocardial creatine in mice demonstrated positive results during ischemic stress. However, it did not prevent chronic heart dysfunction and remodeling in infarcted animals [71, 72].
Further studies examining the effects of elevating both creatine and creatine kinase (CK) levels in myocardial tissue showed that these interventions enhanced systolic function, cardiac output, and survival. However, they did not prevent heart remodeling. These results suggest that while increasing myocardial creatine and CK may improve heart function in the short term, long-term benefits are limited without sustained overexpression of CK [73].
Clinical trials have also shown considerable variability in their results, which makes it challenging to draw definitive conclusions about the role of creatine supplementation in HF. Differences in study designs—such as varying dosages, observation periods, and the inclusion of additional compounds—complicate the interpretation of outcomes. Nevertheless, efforts have been made to gather relevant data to assess the feasibility of creatine supplementation in HF management and whether further research is warranted.
One of the most comprehensive studies in this area was conducted by Cornellisen et al. [74], which examined the effects of creatine supplementation added to aerobic exercise in HF patients. Although physical endurance and peak VO2 improved in both the creatine and placebo groups, no significant differences were observed between the two in any of the primary outcomes. In contrast, Fumagalli et al. [75] conducted a double-blind, randomized study with over sixty patients, demonstrating a statistically significant improvement in quality of life and exercise tolerance in those who supplemented with creatine and coenzyme Q10 (CoQ10) for two months. The doses used were relatively low compared to standard creatine supplementation protocols, and the combined use of CoQ10 raises the question of whether the improvements were primarily due to CoQ10 rather than creatine. This ambiguity is further compounded by inconsistent findings regarding the impact of CoQ10 on exercise capacity, making it difficult to determine which supplement was responsible for the observed benefits.
Kuethe et al. evaluated the effects of creatine supplementation on physical performance, including peak VO2, 6MWT, quality of life, and ejection fraction in a small-scale study. This trial, conducted using a double-blind, crossover design, enrolled 20 patients, of whom 7 were lost to follow-up. Unlike earlier studies, this research found no significant differences between the placebo and experimental groups in physical performance or in the severity of dyspnea, as measured on the Borg scale. However, muscle strength and body weight increased, likely due to the osmotic effects of creatine supplementation. Similarly, the study by Carvalho et al. also found no enhancement in physical performance (6MWT, peak VO2, or perceived exertion on the Borg scale) following creatine supplementation [76]. The small sample sizes in both studies and the fact that Carvalho et al.’s study included only male participants diminish the reliability of these findings. These limitations mean that any subtle effects of creatine supplementation may have been missed.
Beyond investigating creatine’s impact on aerobic capacity and endurance in patients with cardiovascular impairments, some studies have focused on its effect on muscle strength and endurance. Andrews [77] examined the impact of creatine on muscle endurance in HF patients using a forearm handgrip dynamometer. This study found increased exercise tolerance and metabolic responses to physical activity in the male participants. However, the clinical significance of these improvements remains unclear, and the results need to be confirmed in a larger study. Notably, this study used a higher creatine dose (20 grams daily for 5 days) than the standard 5-gram dose, which raises questions about the duration and effectiveness of such a supplementation regimen [77].
In contrast, Gordon et al. [78] investigated the effects of high-dose creatine on muscle endurance and strength (using knee extensors) and ejection fraction in HF patients. No significant differences in physical endurance or ejection fraction were found between the experimental and placebo groups, contrary to the researchers’ expectations based on previous studies. Interestingly, the increase in skeletal muscle creatine levels was more pronounced in patients with initially low creatine levels. This suggests that individuals with low baseline creatine levels might derive a greater benefit from supplementation, particularly in endurance and strength. However, the study’s reliability is questioned due to issues with sample size and the rigor of the blinding process [78].
In conclusion, while there are hints that creatine supplementation may improve cardiac function in HF, the evidence primarily points to its effects on muscle strength rather than physical endurance. Although creatine could theoretically enhance endurance and quality of life for HF patients, there is currently insufficient robust evidence to support this hypothesis.
Creatine’s role in enhancing athletic performance has been widely studied and is gaining increasing attention for its potential in medical research as well. While much of its mechanism is linked to its involvement in the Cr/PCr/ATP system, recent investigations also point to its antioxidant potential [79]. This suggests that creatine may be beneficial for managing oxidative stress, with potential applications in cardiovascular disease [80].
Cardiovascular conditions often result in impaired vascular function, driven mainly by an imbalance in reactive oxygen species (ROS) production, which can damage blood vessels and disrupt normal vascular function. Creatine may offer support through several proposed mechanisms [81].
Given the theoretical benefits, it seems logical to consider creatine supplementation for improving cardiovascular health and recovery, particularly in patients with vascular issues. However, this area remains under-researched, and there is a lack of clinical studies focused on its specific impact on cardiovascular patients.
In an open-label study, De Moraes et al. [82] investigated the effects of creatine supplementation on capillary density and homocysteine levels in young healthy adults. The results showed an increase in capillary density after one week of supplementation. Since reduced capillary density is often associated with hypertension, and restoring capillary networks is linked to managing high blood pressure, this suggests a positive effect of creatine on vascular function [83, 84].
Interestingly, the same study also found a small but statistically significant reduction in mean blood pressure in the creatine group, with no changes in systolic or diastolic pressure. While this reduction was significant (92.1 ± 1.1 mmHg vs. 89.8 ± 1.1 mmHg, P = 0.0255), the clinical importance of this effect remains uncertain. Furthermore, since the study involved normotensive individuals, its relevance for people with hypertension remains to be explored. The study also noted reductions in total and LDL cholesterol levels, a promising sign, as managing cholesterol is a key factor in reducing cardiovascular disease risk [85]. However, homocysteine levels did not change, which contradicts expectations from earlier studies [86, 87]. Notably, plasma creatinine levels were elevated after creatine supplementation.
A study by Van Bavel et al. [88] assessed the impact of creatine supplementation on capillary density in a population of strict vegetarians over three weeks. The results showed a notable increase in basal capillary density. This effect may be more pronounced in individuals with initially low creatine levels, as observed in this vegetarian cohort. Notably, this study also observed a significant reduction in homocysteine levels in the creatine group, in contrast to the study by De Moraes et al. [82], which reported no such change.
Another relevant study by Arciero et al. [89] investigated the combined effect of creatine supplementation and resistance training on body composition, muscle strength, and blood flow in healthy males. This randomized, double-blind study found that adding creatine to resistance training increased fat-free mass and improved blood flow to peripheral areas, like the calf and forearm. Additionally, creatine supplementation alone was associated with an increase in metabolic rate, suggesting it may be effective even without concurrent training. Similar to De Moraes et al. [82], Arciero’s research also found that creatine supplementation lowered blood cholesterol levels significantly (from 172 ± 27 to 155 ± 26 mg/dL, P < 0.01), compared to the placebo group. Despite these promising results, the study did not find evidence that creatine alone influenced vascular function or blood flow. These findings highlight the need for larger, more detailed trials to confirm the clinical relevance of these effects.
Sanchez-Gonzales et al. [90] explored the impact of creatine on vascular responses following isokinetic exercise in healthy young men. This study found that creatine supplementation helped moderate increases in heart rate and systolic blood pressure after exercise, potentially with long-term benefits by reducing strain on the cardiovascular system. However, no differences were noted in the resting parameters before exercise, and the study was limited to young, healthy participants. It is unclear how these findings might translate to individuals with cardiovascular diseases, emphasizing the need for further investigation.
The Cr/PCr/ATP system plays a critical role in the heart’s energy metabolism, particularly during conditions of stress or energy depletion [91]. Therefore, it seems plausible that creatine supplementation could benefit cardiovascular health by enhancing cardiac metabolism. However, existing studies do not yet provide conclusive evidence to support creatine as an effective treatment for cardiovascular diseases. While some research suggests potential cardiovascular benefits, such as improved cholesterol levels or vascular health [75, 82, 89], these studies have mainly involved healthy individuals. Consequently, the data are insufficient to recommend creatine supplementation for cardiovascular patients at this time.
Despite this, creatine remains an attractive supplement due to its low cost, widespread availability, and minimal side effects compared to traditional cardiology drugs. The possibility that creatine could enhance performance in patients with cardiovascular disease, as seen in athletes, remains a compelling avenue for future research. Unfortunately, current studies have not shown significant benefits in cardiovascular patients, but this area warrants further investigation through large, well-designed randomized trials to clarify its potential.
Undoubtedly, creatine has become one of the most widely used and extensively studied supplements, particularly in sports, where extensive research has validated its benefits. Its critical role in energy metabolism has sparked interest in its potential applications beyond athletics, leading to an influx of studies exploring its possible therapeutic effects in various health conditions. However, despite the promising body of research, specific flaws in study designs, such as small sample sizes and inconsistencies, complicate the ability to draw definitive conclusions.
From a practical standpoint, creatine supplementation offers both advantages and drawbacks. One significant benefit is its affordability and widespread availability, coupled with a favorable safety profile when used within recommended dosages [3, 5]. It also comes in multiple forms, such as pills, powders, and beverages, providing users with flexibility to choose the most convenient format [8, 12]. However, there are some limitations to consider. A portion of the population, known as non-responders, may have difficulty effectively utilizing creatine, resulting in less noticeable benefits [92]. Additionally, water retention is a common side effect, which can be particularly undesirable for cardiovascular (CV) patients who are already prone to edema [5]. Another consideration is that creatine levels typically return to baseline within 4-6 weeks after discontinuation, suggesting that sustained benefits require consistent long-term use [3].
Beyond the cardiovascular realm, creatine’s potential benefits have been explored in several other health conditions, though many of the results remain inconclusive. For instance, creatine supplementation has been investigated in neurodegenerative diseases such as Huntington’s disease and Parkinson’s disease. Although initial studies showed promising results, subsequent placebo-controlled randomized trials failed to demonstrate significant improvements in patient outcomes [93, 94]. Similar findings were observed in studies involving amyotrophic lateral sclerosis (ALS) [95]. On the other hand, in the case of muscular dystrophies, a Cochrane Library meta-analysis found that creatine supplementation improved muscle strength and overall function, with no clinically significant adverse effects [96].
Creatine has also been studied for its potential role in geriatrics, particularly in conditions like osteoporosis, sarcopenia, and cachexia, which are prevalent in older populations. Research suggests that creatine supplementation, especially when combined with resistance training, may help mitigate the adverse effects of aging on muscle health [97]. Notably, creatine supplementation has been shown to improve sit-to-stand performance in older adults, a clinical outcome strongly associated with reduced fall risk [98, 99]. However, the evidence regarding creatine’s impact on bone health is less clear [97, 100]. Since bone remodeling is a prolonged process, further long-term studies are needed better to understand its potential benefits for individuals with osteoporosis.
Considering the role of the Cr/PCr/ATP shuttle and the pathophysiology of the conditions discussed in this review, creatine supplementation appears to be a reasonable and promising intervention for these diseases. However, the wide range of studies conducted to date has yielded inconsistent results. Challenges such as study design flaws and small sample sizes make it difficult to draw clear conclusions. Therefore, future research should aim to address these limitations. The coming years will reveal whether the anticipated benefits of creatine supplementation in these contexts are realized or if further investigation is needed.
None
None
None
None
Open Access The author(s) retain copyright. This article is licensed under the Creative Commons Attribution-NonCommercial-ShareAlike 4.0 International License. It may be shared and adapted for non-commercial purposes with appropriate attribution, an indication of changes, and distribution of adaptations under the same license. Third-party material may be subject to separate terms identified in its credit line. View the license at https://creativecommons.org/licenses/by-nc-sa/4.0/.
 Publication System

